On Sunday, November 11, 2018, doctors are reportedly holding a protest in front of Deoksugung Palace, across from Seoul City Hall. Doctors, who should be studying hard and staying by the side of patients in pain, should never have to take to the streets. And yet I, too, plan to join tomorrow.
Medicine Is a Science, and Still Largely Uncharted Territory
Everyone makes mistakes. Doctors are human. So doctors make mistakes too. And doctors cannot save everyone who is going to die. Why is there a misdiagnosis rate? Many people mistakenly believe it is because doctors lack skill or are negligent.
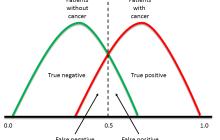
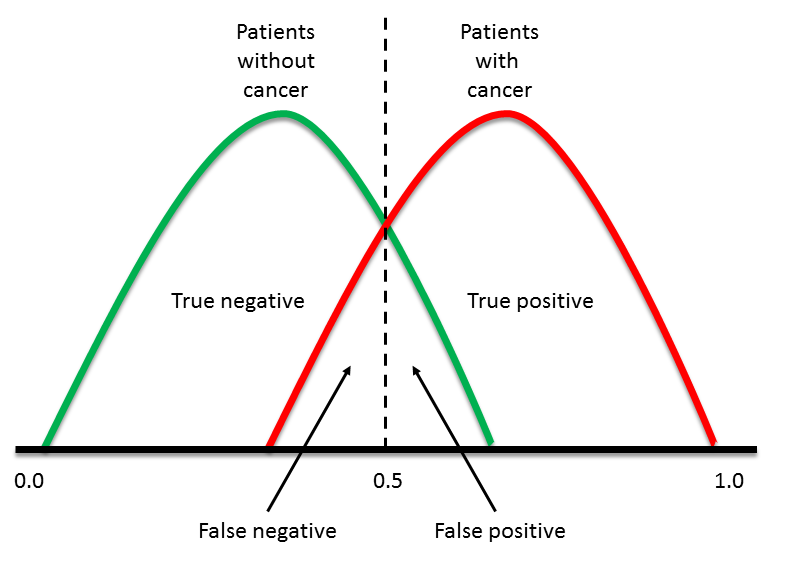
For example, how high does a tumor marker level in the blood have to be before cancer is diagnosed? The distribution and average of tumor marker levels differ between healthy people and people with cancer. But the two overlap to some extent, and depending on which threshold (cut-off value) is chosen for diagnosing cancer, sensitivity and specificity change, and so does the accuracy of the test. If the threshold is too low, there are more positive diagnoses and therefore more false positives. If it is too high, there are more negative diagnoses and false negatives increase. That is why there is always a margin of error in diagnosis.
The reliability of a particular medical device is assessed by measuring its sensitivity and specificity, and when a device is manufactured, this is measured by comparing it with the method regarded as the gold standard.
Sensitivity: the probability that a person who actually has the disease tests positive
Specificity: the probability that a person who does not have the disease tests negative
Accuracy: Sensitivity + Specificity / 2
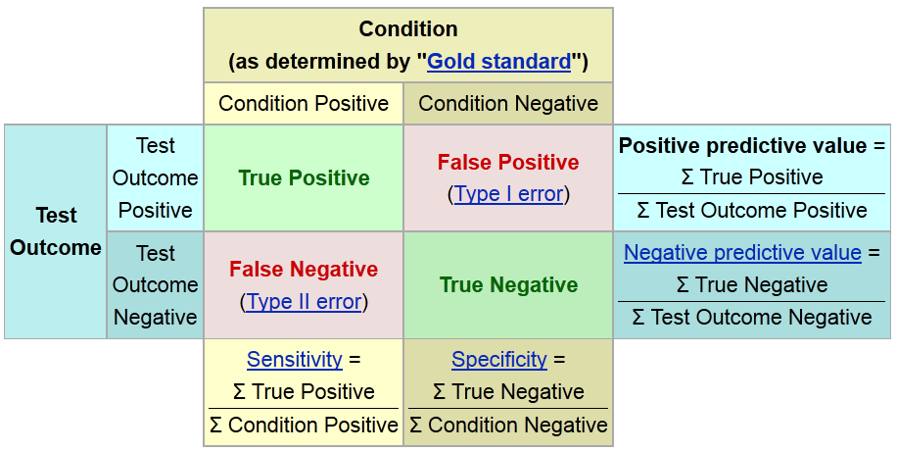
Let us assume that, when it comes to diagnosing disease, a doctor is also a kind of diagnostic machine. With enough evidence and test results, accuracy increases, but there will always be false positives and false negatives in diagnosis. To begin, let us assume that a particular machine or doctor has a sensitivity of 0.95 and a specificity of 0.95 for a particular disease.
Suppose one disease is common, with 40,000 patients per 100,000 people, and another is uncommon, with 2,000 patients per 100,000 people.
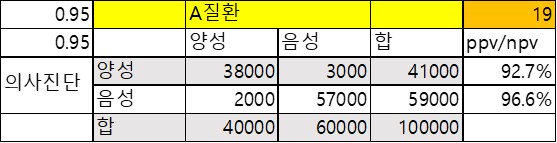
When 40,000 out of 100,000 people (40%) have Disease A, if a device or doctor with 95% accuracy gives a positive diagnosis, the probability that the person truly has the disease is about 92.7%.
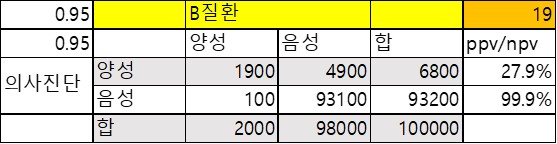
When 2,000 out of 100,000 people (2%) have Disease B, if a device or doctor with 95% accuracy gives a positive diagnosis, the probability that the person truly has the disease drops to about 27.9%.
For Disease B, with a prevalence of about 2%, when a device or doctor with 95% accuracy diagnoses cancer, only about 27.9% of those cases are actually cancer — that much misdiagnosis occurs — and 4,900 out of every 100,000 people will undergo additional examinations and treatment.
Screening Tests
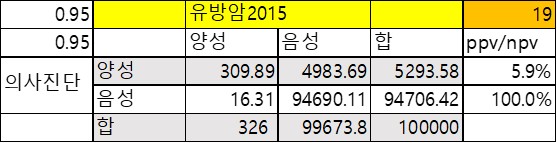
When 326.2 out of 100,000 people (0.33%) have breast cancer, if a device or doctor with 95% accuracy gives a positive diagnosis, the probability that it is truly cancer is only about 5.9%; on the other hand, a negative result can be trusted almost 100%.
In 2015, the prevalence of breast cancer in Korea was 326.2 per 100,000 people. When screening with mammography of 95% accuracy, the posterior probability is only 5.9%. In addition, there are 4,984 false positives and about 16 missed cases, so even when the result is positive, 94% are not cancer, and a negative result is not 100% either. That is why screening tests use methods that are as sensitive as possible, inexpensive, and simple.
In other words, no matter how skilled the doctor, if the accuracy of a positive diagnosis for a rare disease is below 50%, it has no value and the result should not simply be accepted. Of course, people who test negative can be confident they do not have the disease, so it cannot be said that the test is not worth taking. But patients who receive a false-positive diagnosis will need additional tests for confirmation, and most of those results will come back negative. In the end, to avoid missing the disease in a small number of patients, the people with false positives become victims who undergo unnecessary tests.
However, the value of a screening test lies in narrowing the target group from a total of 100,000 people down to 5,294. The 5,294 people who screened positive then undergo further testing for a definitive diagnosis. This time, tests with the highest possible specificity are chosen. These are usually expensive and complex, but by reducing false positives as much as possible, a positive result can accurately indicate that the disease is truly present.
On the Judge's Decision to Jail Doctors over the Scientific Error Inherent in Diagnosis
In 2015, Korea had 2.3 million people aged 5 to 10, and reportedly 2 of them were diagnosed with acquired diaphragmatic hernia.
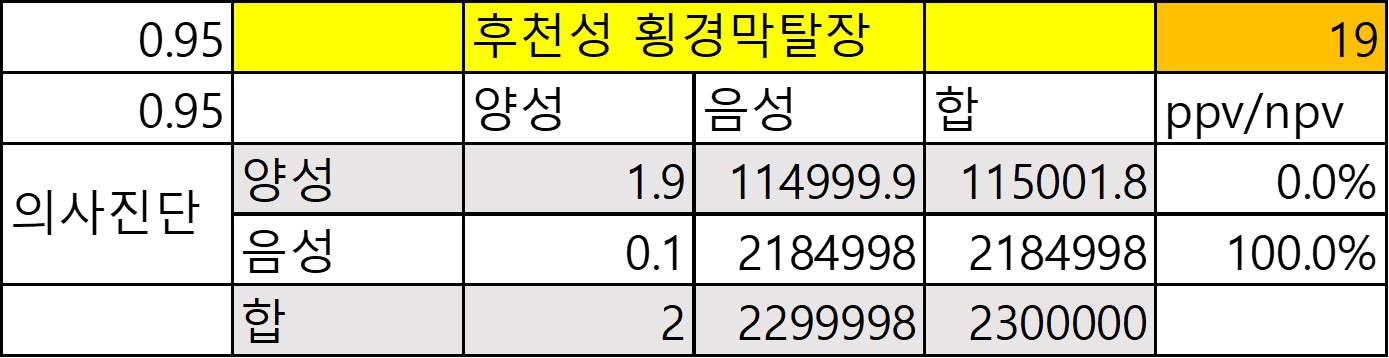
In normal practice, a total of 115,000 people would be judged positive, and fewer than 2 of them would actually have the disease, so the probability that a person with a positive diagnosis truly has it is close to 0%. The remaining 115,000 false positives would have to be admitted to hospital and undergo CT scans for confirmation. In that situation, even if there were findings suggestive of diaphragmatic hernia, the chance of being wrong was higher, so it was a reasonable decision for the doctor to send home a patient whose symptoms had improved.
Acquired diaphragmatic hernia is an extremely rare disease. In Korea, its prevalence is about 1 in 1 million people. That means even if a highly skilled and reliable machine or doctor gives a positive diagnosis, the probability that it is a false positive — that is, wrong — is higher. Even so, if a doctor, confident in his own skill, admitted everyone suspected of diaphragmatic hernia and ordered CT scans, the Health Insurance Review and Assessment Service of Korea's national health insurance system would brand him a money-seeking doctor engaged in fraudulent and excessive treatment, and the doctor would have to pay back all the costs.
So even though there was such a finding on the X-ray, the probability of it being a true case was nearly 0%. The doctor therefore diagnosed constipation, the most common cause of abdominal pain in that age group, gave an enema, and sent the patient home after the symptoms improved. This is a diagnostic approach that every doctor has internalized.
The judge who jailed the doctors in this case must apologize to doctors. And the state must compensate doctors for the harm done.
The Usefulness of Regular Breast Cancer Screening for Women Aged 50 and Over
In fact, a study by the international Cochrane Collaboration of more than 600,000 people aged 50 and over found that with regular breast cancer screening, 4 per 1,000 people died of breast cancer over 10 years, while without screening, 5 per 1,000 died over 10 years.
The conclusion is that breast cancer screening improved mortality by about 0.1%, while producing about 100 false positives per 1,000 people, leading to additional unnecessary biopsies. For this reason, regular breast cancer screening is not performed in Europe, whereas in Korea the National Health Insurance Service provides it.
Dr. Jung, Director, Venus Clinic